

Category: Medication safety

  • Pharmacist wearing a turban working at a computer in a pharmacy store with shelves filled with medicine.

    Polypharmacy, falls and deprescribing: what caregivers see first

    Read this first. Nothing here is a reason to stop or reduce any medication. Several of the drugs discussed are dangerous to withdraw abruptly, and some must be tapered under supervision. This article exists to help you notice and report — the decision belongs to the prescribing clinician.

    Polypharmacy, commonly defined as five or more regular medications, leads to falls through orthostatic hypotension, a drop in blood pressure on standing for which medications are the leading contributor. Caregivers see it first as gray-out on standing or a hand reaching for furniture; the right response is to report it and ask for a medication review, never to stop a drug.

    Our attendants and the families we work with spend hours a day in the same homes. They are the ones who see someone steady themselves on the door frame getting out of bed, or sit back down halfway through standing up. Almost none of that reaches a clinic, because a blood pressure taken seated in an office after a five-minute rest is a measurement of a situation that never happens at home.

    That gap matters, because the medication list is among the most common reversible causes of serious harm in later life — and the earliest signs of it are behavioral, not numerical.

    How does polypharmacy happen in older adults?

    Polypharmacy — commonly defined as five or more regular medications — is rarely the result of a single bad decision. It is the accumulated residue of many reasonable ones.

    A cardiologist starts a blood pressure medication. A year later a hospital adds a second during an admission. A primary care physician adds a statin. A urologist adds an alpha-blocker. Each prescriber is acting correctly within their own remit, each drug was right on the day it was written, and nobody owns the list as a whole. Meanwhile the person taking it has lost fifteen pounds, become less active, and their kidneys clear drugs more slowly than they did at 68.

    The dose has not changed. The patient has.

    How does polypharmacy cause falls?

    This is the pathway worth understanding properly, because it is the one that ends in a hip fracture.

    Orthostatic hypotension is a fall in blood pressure on standing — formally, a drop of at least 20 mmHg systolic or 10 mmHg diastolic within three minutes of standing up. It affects roughly one in five community-dwelling older adults, and reviews of the condition identify medications as the leading contributing factor.

    What it looks like in a home is not a number. It is a few seconds of gray-out on standing, a hand reaching for furniture, a complaint of lightheadedness on the way to the bathroom at night. Some people get aching across the neck and shoulders — the so-called coat-hanger distribution — or blurred vision rather than obvious dizziness.

    The consequences are not proportionate to how minor it looks. Orthostatic hypotension is associated with a substantial increase in falls, and reviews report up to a 50 percent increase in the relative risk of all-cause mortality. A hip fracture at 80 carries a risk of death and of permanent loss of independence that has nothing to do with blood pressure at all. The medication preventing a stroke can cause the event that ends independent living.

    Antihypertensives: named in the guidelines, specifically

    This is not a fringe concern raised by skeptics. Two of the most widely used prescribing-safety frameworks in geriatric medicine call out particular blood pressure drug classes by name.

    • The AGS Beers Criteria — the American Geriatrics Society’s expert-consensus list of medications often inappropriate in older adults — identifies a high risk of orthostatic hypotension and related harms with certain antihypertensive classes, and does not recommend them as routine treatment for hypertension in this population.
    • The STOPP/START criteria, updated to their third version in 2023, recommend stopping alpha-blockers and centrally acting agents in people at risk of falls, precisely because the resulting vasodilation produces postural hypotension.

    Neither framework argues that older people should not have their blood pressure treated. Both argue that which drug, at what dose, deserves review as the person changes.

    More on blood pressure monitoring in older adults →

    Statins: a real trade-off, not a scandal

    Statins deserve a place in this discussion for a different reason, and it is one that gets lost between two bad arguments — that they are miracle drugs, or that they are a fraud. Neither is true.

    Statins increase the risk of new-onset type 2 diabetes. This is established and uncontested:

    • In February 2012 the FDA added a class-wide safety label change to statins, warning of increases in HbA1c and fasting blood glucose.
    • A collaborative meta-analysis of randomized statin trials published in The Lancet in 2010 found roughly a 9 percent increase in incident diabetes.
    • An individual-participant-data meta-analysis published in 2024 in The Lancet Diabetes & Endocrinology confirmed effects on both new-onset diabetes and worsening glycemic control.

    The risk is higher with intensive dosing and concentrated in people already near the diabetes threshold — which describes a large share of the older population. Cardiology bodies including the American College of Cardiology hold that for patients at meaningful cardiovascular risk the benefit still outweighs this harm, and that remains the mainstream position.

    But “outweighs” describes a trade-off, not an absence of harm. A person taking a statin for primary prevention at 84, with a limited life expectancy and a fasting glucose creeping upward, is in a genuinely different position from a 58-year-old who has already had a heart attack. Both may be prescribed the same drug.

    More on cholesterol in older adults →

    What is deprescribing?

    Deprescribing — the planned, supervised reduction or withdrawal of medication that no longer earns its place — is not the absence of treatment. It is a recognized part of good geriatric practice, with published instruments behind it.

    • AGS Beers Criteria. Medications often inappropriate in older adults because harms outweigh benefits at that age.
    • STOPP/START, version 3 (2023). A systems-based review covering both potentially inappropriate medications and potential prescribing omissions — it flags what is missing as readily as what should stop.
    • STOPPFrail. Aimed at people with limited life expectancy, where a preventive medication’s time to benefit may exceed the time available.

    That last concept is the one families find most clarifying. A drug that prevents events over ten years offers little to someone whose prognosis is two — while its side effects, including falls, arrive immediately. Weighing that is a clinical judgment, but it is a legitimate one, not a form of giving up.

    What are the warning signs of polypharmacy?

    This is the part that belongs to whoever is in the house. None of it requires clinical training — it requires being present and paying attention.

    Report promptly

    • Dizziness or gray-out on standing
    • Grabbing furniture or walls to steady up
    • Any fall, or near-fall — including ones dismissed as clumsiness
    • Fainting, however briefly
    • New confusion or unusual drowsiness
    • Increasing thirst or urination

    Also worth mentioning

    • Symptoms that started after a dose change
    • Falls clustered in the morning or after naps
    • Doses skipped because they “make me feel funny”
    • Two prescribers who may not know about each other
    • Pills left in the organizer at the end of the week
    • A list nobody has reviewed in years

    Timing is diagnostic information. “She gets dizzy” is a symptom. “She gets dizzy standing up from the edge of the bed, most mornings, and it started about three weeks after the new tablet” is close to a diagnosis. Write down what you saw and when — memory compresses and reshapes this kind of detail within days.

    How do you ask for a medication review?

    Families are often unsure whether they are allowed to raise this. They are. A structured medication review is ordinary care, not a challenge to the prescriber.

    1. Gather everything into one bag — prescriptions, over-the-counter medicines, supplements, eye drops, creams, and anything prescribed by a specialist the primary physician may not know about. Supplements matter; they interact.
    2. Take the bag to the appointment rather than a list from memory. What is in the cupboard and what is on the record are frequently different.
    3. Bring your written observations — dates, times of day, what happened.
    4. Ask three questions: what is each of these still for; which of them could be contributing to the dizziness or falls; and is there anything here we could reduce or stop.
    5. Ask what to expect if something is changed, and what should prompt a call back.

    What not to do

    Never stop or reduce a medication on your own, and never advise someone you care for to do so. Stopping an antihypertensive abruptly can cause rebound hypertension. Several classes must be tapered. Stopping a statin after a cardiac event is a different and far riskier proposition than never starting one. Personal care attendants do not advise on medication at all — if the person you care for raises doubts, the right response is to encourage them to take it to their clinician, and to report what you have observed.

    What this means for day-to-day care. Attendants are frequently the only person who sees the same individual every morning for months. That vantage point is genuinely rare in healthcare, and it is why the observation above is worth taking seriously rather than filing as complaining. A pattern noticed in a hallway in February and reported plainly is worth more to a prescriber than another office blood pressure reading.

    Frequently asked questions

    What is polypharmacy?

    Polypharmacy is commonly defined as taking five or more regular medications. It rarely comes from one bad decision. A cardiologist, a hospital, a primary care physician and a urologist each add a drug that was right on the day it was written, and nobody owns the list as a whole. The list grows while the person taking it changes.

    Who is most likely to have problems with polypharmacy?

    The person whose body has changed while the doses have not. Someone who has lost weight, become less active, or whose kidneys now clear drugs more slowly is taking the same pills into a different body. Risk also rises when two prescribers may not know about each other, and when nobody has reviewed the list in years.

    What is orthostatic hypotension?

    It is a drop in blood pressure on standing: at least 20 mmHg systolic or 10 mmHg diastolic within three minutes of standing up. It affects roughly one in five older adults living at home, and medications are the leading contributor. At home it looks like gray-out on standing, a hand reaching for furniture, or lightheadedness at night.

    Should I stop a medication that makes my parent dizzy?

    No. Never stop or reduce a medication on your own, and never advise someone you care for to do so. Stopping a blood pressure drug abruptly can cause rebound hypertension, and several drug classes must be tapered. Write down what you saw and when, report it, and ask the prescribing clinician for a medication review.

    Sources

    This article is general information, not medical advice. It describes published research; it is not a recommendation for you or the person you care for. Never start, stop or change a prescribed medication because of something you read here — talk to the prescribing clinician first. Communicare Elite provides non-medical personal care through Missouri’s Consumer Directed Services program and does not provide medical advice or treatment.
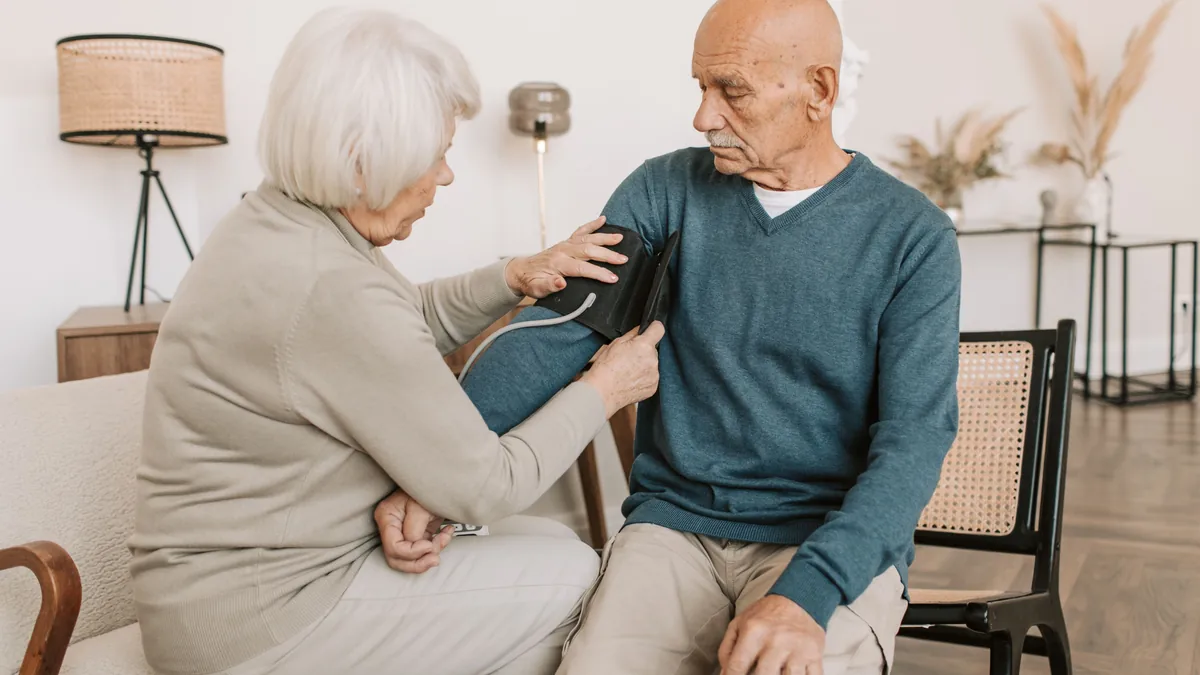

  • An older woman checks her husband's blood pressure with an upper-arm cuff at home

    Blood pressure medication in older adults: the case for monitoring

    Read this first. High blood pressure is a serious condition and treating it prevents strokes and heart attacks. Nothing on this page is a reason to stop or reduce a blood pressure medication. Stopping antihypertensive medication without medical supervision can be dangerous. The point of this article is that treatment needs ongoing review — which is a reason to talk to a clinician, not to act alone.

    Blood pressure medication in older adults needs ongoing monitoring, because a dose that was right at 68 can be too much at 78. A study in Age and Ageing of more than 11,000 patients over 70 found over 1,200 taking antihypertensives while measuring hypotensive, and linked persistent low blood pressure in this group to increased mortality and hospital admission.

    Hypertension is one of the most common conditions in older adults; research has put the prevalence among Western populations over 60 at around 60 percent. It is so routine that the diagnosis, once made, often stops being questioned — and so does the prescription.

    What did the study find about blood pressure medication after 70?

    A study published in Age and Ageing analyzed more than 11,000 patients over the age of 70 and found that a substantial number — over 1,200 of them — were taking antihypertensive medication while measuring hypotensive, meaning their blood pressure was below the normal range rather than above it.

    The researchers linked persistent low blood pressure in this group to increased mortality and hospital admission.

    Why can a blood pressure dose become too strong with age?

    It is rarely anyone’s mistake in particular. It is what happens when a correct decision is never revisited. Blood pressure genuinely falls with age, with weight loss, with illness, and with reduced activity. A dose that was right at 68 can be too much at 78, and nobody notices unless somebody measures.

    The consequences of overshooting are not abstract in an older person: dizziness on standing, falls, fainting, confusion, and hospital admissions that follow from those.

    Can blood pressure medication cause falls in older adults?

    It is worth spelling out the mechanism, because “blood pressure a bit low” sounds harmless and the endpoint is not.

    An antihypertensive dose that is too much for the person taking it produces orthostatic hypotension — blood pressure dropping on standing. That causes dizziness, unsteadiness and fainting, most often on getting out of bed or up from a low chair. In an older adult that means falls; falls mean fractures and head injuries; and a hip fracture at 80 carries a mortality and loss-of-independence risk that has nothing to do with blood pressure at all. The drug that was preventing a stroke can end up causing the event that ends independent living.

    Geriatric medicine treats this as a named, actionable problem rather than bad luck. Both the AGS Beers Criteria and the STOPP/START criteria flag medication classes for exactly this reason — centrally acting antihypertensives and alpha-blockers in particular are singled out for causing postural hypotension and falls, and are not recommended as routine treatment for hypertension in older adults.

    What is deprescribing blood pressure medication?

    There is a formal body of practice around reducing or stopping medications that no longer earn their place, and it applies to antihypertensives specifically. Published tools — Beers, STOPP/START, and STOPPFrail for people with limited life expectancy — exist to identify candidates for review, and there is trial evidence on structured withdrawal rather than guesswork.

    The point is not that older people should be on fewer blood pressure medicines as a rule. It is that the decision deserves the same deliberate attention going down as it got going up, and that in practice it rarely gets it. A dose set at 68 is often still running unexamined at 82, after twenty pounds of weight loss and a decline in activity that both lower blood pressure on their own.

    Deprescribing is something a clinician does with you, never something to attempt alone. Stopping an antihypertensive abruptly can cause rebound hypertension, and some of these drugs must be tapered. The action this article is asking for is a conversation, not a decision.

    Should older adults stop taking blood pressure medication?

    No. The researchers called for reviewing treatment, not stopping it: consistent follow-up after starting or changing an antihypertensive, and awareness that hypotension is a real risk in a frail population, not just hypertension.

    Why this matters more in home care than in a clinic

    Blood pressure is measured in a clinic, sitting down, after a rest. The problems caused by it being too low happen somewhere else entirely — standing up from a low chair, getting out of bed at 3 a.m., turning quickly in a bathroom. A reading taken in the right conditions can look perfectly acceptable while the person is nearly fainting at home every morning.

    This is called orthostatic hypotension — a drop in blood pressure on standing — and it is both common and under-detected in older adults. It is also one of the most direct causes of the falls that end independent living. The information that closes the gap between the clinic reading and the reality is behavioral, and it comes from whoever is in the house.

    What this means for day-to-day care. This is one of the clearest examples of why the person who is there every day matters. Dizziness when standing up, unsteadiness after getting out of bed, new confusion, near-faints, or a pattern of falls in the morning are all worth reporting to the family and the person’s clinician. A personal care attendant does not administer medication or make clinical judgments — but noticing and reporting a pattern is exactly the kind of information that gets a dose reviewed.

    Frequently asked questions

    What are the signs that blood pressure medication is too strong?

    Watch for dizziness when standing up, unsteadiness after getting out of bed, fainting or near-faints, new confusion, and falls, especially a pattern of falls in the morning. These point to blood pressure dropping on standing, called orthostatic hypotension. A reading taken sitting down in a clinic can look normal while the person is nearly fainting at home every morning.

    What blood pressure medications are older adults told to avoid?

    Two geriatric prescribing tools, the AGS Beers Criteria and the STOPP/START criteria, single out centrally acting antihypertensives and alpha-blockers. Both classes are known for making blood pressure drop on standing, which leads to falls, and neither is recommended as routine treatment for high blood pressure in older adults. Any change belongs with the prescribing clinician.

    Can an older adult stop blood pressure medication on their own?

    No. Stopping an antihypertensive abruptly can cause rebound high blood pressure, and some of these drugs must be tapered. Reducing or stopping a medication, called deprescribing, is something a clinician does with the patient, using published tools such as Beers, STOPP/START and STOPPFrail. The right step is to ask the prescriber for a review.

    Why does blood pressure medication need to be reviewed as you get older?

    Blood pressure falls on its own with age, weight loss, illness and less activity, so a dose that was right at 68 can be too much at 78. A study in Age and Ageing of more than 11,000 patients over 70 found over 1,200 taking blood pressure medication while their pressure was already low, and linked that to more deaths and hospital admissions.

    How can a home caregiver help with blood pressure medication safety?

    A personal care attendant does not give medication or make clinical judgments, but they see what a clinic visit misses. Dizziness on standing, unsteadiness after getting up, new confusion, near-faints or morning falls are worth reporting to the family and the person’s clinician. Noticing and reporting that pattern is exactly the information that gets a dose reviewed.

    Sources

    This article is general information, not medical advice. It describes published research; it is not a recommendation for you or the person you care for. Never start, stop or change a prescribed medication because of something you read here — talk to the prescribing clinician first. Communicare Elite provides non-medical personal care through Missouri’s Consumer Directed Services program and does not provide medical advice or treatment.

  • A healthcare worker examining a senior man at home with face masks during the pandemic.

    Cholesterol in older adults: what the debate is actually about

    Read this first. Statins and other cholesterol-lowering medicines are prescribed to prevent heart attacks and strokes, and large randomized trials show they do. Do not stop, reduce or skip a cholesterol medication because of anything on this page. If you have questions about whether yours is still right for you, that is a conversation to have with the clinician who prescribed it.

    The debate is about a 2016 BMJ Open review of 19 cohort studies, about 68,000 older people, which reported that high LDL cholesterol was mostly not associated with higher all-cause mortality. Critics, including the Oxford Centre for Evidence-Based Medicine, faulted its method, and randomized trials of cholesterol-lowering therapy consistently show fewer heart attacks and strokes.

    An earlier version of this article presented one side of a contested question as settled fact, and told readers that statin benefits were “grossly exaggerated.” That was not a fair summary of the evidence, and it has been rewritten.

    Is high LDL cholesterol linked to death in older adults?

    In 2016 a group led by Uffe Ravnskov published a systematic review in BMJ Open covering 19 cohort studies — about 68,000 older people in total. The authors reported that in most of the cohorts they examined, high LDL cholesterol was not associated with higher all-cause mortality, and in a number of cohorts the association ran the other way: higher LDL, lower mortality.

    Why it was criticized

    Heavily, and by mainstream bodies. The main objections:

    • Method. The Oxford Centre for Evidence-Based Medicine and others argued the review relied on aggregated published summaries rather than individual participant data, an approach prone to bias, and that its selection and analysis were not robust.
    • It contradicts trial evidence. Observational associations between cholesterol level and death are not the same thing as testing what happens when you lower it. Randomized trials of cholesterol-lowering therapy consistently show reduced heart attacks and strokes, including in older participants.
    • Reverse causation is a known trap here. Serious illness — cancer, frailty, advanced heart failure — lowers cholesterol. In an elderly cohort, low LDL can be a marker of being ill rather than a cause of dying, which can manufacture an apparent inverse association.

    Do statins raise the risk of type 2 diabetes?

    The statin debate is often framed as “do they work or not,” which misses the more useful question of what they cost. One documented cost belongs in any honest discussion, and the first version of this article left it out entirely.

    Statins raise the risk of new-onset type 2 diabetes. This is not a contested claim. In February 2012 the FDA added a safety label change to the entire statin class warning of increases in HbA1c and fasting blood glucose. A collaborative meta-analysis of randomized statin trials published in The Lancet in 2010 found roughly a 9 percent increase in incident diabetes, and a 2024 individual-participant-data meta-analysis in The Lancet Diabetes & Endocrinology confirmed effects on both new-onset diabetes and worsening glycemic control.

    The risk is not evenly spread. It is higher with intensive-dose therapy and concentrated in people who already sit close to the diabetes threshold — which, in an older population, is a great many of them. Cardiology bodies including the American College of Cardiology hold that for patients at meaningful cardiovascular risk the benefit still outweighs this harm, and that remains the mainstream position. But “outweighs” is a trade-off, not an absence of harm, and a trade-off is something a patient is entitled to know they are making.

    How do doctors decide if an older adult still needs a statin?

    The most useful frame for an older adult is not whether statins work in general but whether this medication, at this dose, still earns its place on a list that may run to a dozen drugs. Geriatric medicine has formal tools for exactly that question.

    • The AGS Beers Criteria, an expert-consensus list of medications that are often inappropriate in older adults because the harms outweigh the benefits at that age.
    • The STOPP/START criteria, now in their third version (2023), covering drug-drug and drug-disease interactions, therapeutic duplication, medications that specifically raise falls risk, and treatments that are wrongly omitted.
    • STOPPFrail, aimed at people with limited life expectancy, where the years needed for a preventive medication to pay off may exceed the years available.

    None of these tools says “stop your statin.” What they do is make periodic review a normal part of care rather than something that only happens after a fall or an admission. If nobody has revisited a prescription in several years, that is worth raising — and it is a very different conversation from stopping the drug yourself.

    Should an 80-year-old start taking statins?

    There is a real and legitimate clinical question underneath the controversy, and it is narrower than the headlines: how much benefit does starting a statin for primary prevention give someone in their late 80s with a limited life expectancy and a long list of other medications? Guidelines are genuinely more cautious there, and deprescribing is an accepted part of good geriatric practice.

    That is a very different proposition from stopping a statin in someone who has already had a heart attack. “Is this still the right medication for me?” is a good question to bring to a clinician. “I read online that cholesterol does not matter” is not a plan.

    What this means for day-to-day care. Personal care attendants do not advise on medication and should not be drawn into it. If the person you care for raises doubts about their prescriptions, the right response is to encourage them to raise it with their clinician or their family — not to agree, disagree, or look it up for them. What is worth reporting is practical: pills going untaken, confusion about doses, or new side effects like muscle pain.

    Frequently asked questions

    Can you stop taking statins on your own?

    Do not stop, reduce or skip a cholesterol medication because of something you read. Whether a statin is still right for you is a question for the clinician who prescribed it. Periodic review is a normal part of geriatric care, and tools such as the Beers Criteria, STOPP/START and STOPPFrail exist to guide it, but the review is a conversation with the prescriber, not a decision made alone.

    What did the 2016 review of cholesterol in older people find?

    A 2016 BMJ Open review led by Uffe Ravnskov covered 19 cohort studies and about 68,000 older people. In most of those cohorts, high LDL cholesterol was not associated with higher death from all causes, and in a number of them the association ran the other way: higher LDL went with lower mortality.

    Why are statins questioned for people in their late 80s?

    The open question is how much benefit starting a statin for prevention gives someone in their late 80s with limited life expectancy and a long list of other medications. Guidelines are more cautious there. STOPPFrail was built for exactly this case, where the years a preventive drug needs to pay off may be more than the years available.

    What are the side effects of statins in older adults?

    Statins raise the risk of new-onset type 2 diabetes. In 2012 the FDA added a warning to the whole statin class about rising HbA1c and fasting blood sugar. The risk is higher with intensive doses and in people already close to the diabetes threshold, which describes many older adults. Muscle pain is another side effect worth reporting to the prescriber.

    What should a caregiver report about statins?

    Personal care attendants do not advise on medication. If the person raises doubts about a prescription, encourage them to talk with their clinician or family rather than agreeing, disagreeing or looking it up for them. What is worth reporting is practical: pills going untaken, confusion about doses, and new side effects such as muscle pain.

    Sources

    This article is general information, not medical advice. It describes published research; it is not a recommendation for you or the person you care for. Never start, stop or change a prescribed medication because of something you read here — talk to the prescribing clinician first. Communicare Elite provides non-medical personal care through Missouri’s Consumer Directed Services program and does not provide medical advice or treatment.